
An effective SDOH screening workflow pairs a standardized screening tool with EHR-coded data capture and a closed-loop referral path that tracks referral acceptance and resolution. That means naming who screens, who scores, and who follows up, then mapping each answer to a code your system can report on. Programs ready to pilot should pick one validated tool and one referral pathway, then expand once the workflow holds up under real patient volume.
TL;DR:
- Using a validated screening tool like AHC HRSN or PRAPARE and linking responses to LOINC codes is essential for standardized data collection and reporting.
- Embedding screening workflows into pre-visit portals, check-in, or verbal administration ensures high reach and accommodates patient preferences.
- A closed-loop referral system with documented status updates from sent to resolved is critical for measuring follow-up and program effectiveness.
- Staff roles must be clearly assigned, with training and role boundaries established before implementation to prevent burnout and workflow stalls.
- Metrics such as screening rate, referral acceptance, and closed-loop completion are necessary to track progress and comply with CMS measures.
Table of Contents
- Choosing your screening scope and instrument
- Mapping the workflow from check-in to follow-up
- Embedding the screener in your EHR and mapping the codes
- Designing a referral path that actually closes
- Aligning your metrics with CMS measures and program goals
- Anticipating the barriers that stall most pilots
- What the evidence says about closing the loop
- How EquiLoop and Workforce Development Academy can support your rollout
- Sources
- FAQ
Choosing your screening scope and instrument
Universal screening asks every patient the same questions at every visit. Targeted screening focuses on a subpopulation, a single condition, or a specific domain, and it demands less staff time but misses patients outside the target group. Most programs starting from zero do better piloting a targeted or single-domain approach before expanding, since it limits the volume of positive screens a small referral network has to absorb.
Whichever scope you choose, the Accountable Health Communities (AHC) HRSN Screening Tool defines five core domains: living situation, food, transportation, utilities, and interpersonal safety, and maps each item to a LOINC code for standardized data exchange. PRAPARE covers similar ground with more supplemental items, including domains like education, employment, and social isolation, which suits organizations that need a fuller social profile for care planning rather than a lean measure-reporting instrument.
- AHC HRSN fits teams prioritizing CMS measure alignment and a shorter, standardized instrument.
- PRAPARE fits teams that want broader domain coverage for care planning, especially in community health center settings.
- Supplemental domains (education, employment, social isolation, health literacy) can be added to either tool without disrupting the core five.
- Both tools carry LOINC mappings, so confirm you are using the current citation and coding guidance before embedding items into a form.
If you adapt or reuse screening items outside a CMS or AHC Model context, check the citation and notification requirements tied to the tool, since some items require attribution or notice to the original authors. A closer look at instrument trade-offs, including administration time and scoring logic, is available in our screening tools guide.
Mapping the workflow from check-in to follow-up
A screening workflow only works if every step has an owner and a deadline. Below is a sequence that scales from a single clinic to a multi-site network.
- Offer screening pre-visit through a patient portal or text message when available, since this reduces waiting-room burden but requires patients with digital access and comfort with the format.
- Fall back to check-in or rooming for patients without portal access, using a tablet or paper form that staff can scan into the chart.
- Let clinical staff administer screening verbally for patients who prefer or need help with reading, especially during rooming when a medical assistant already has the patient’s attention.
- Route positive screens immediately to a navigator or community health worker (CHW) rather than waiting for the clinician visit to conclude, particularly for safety-related flags.
- Document a brief intro script so every staff member introduces screening the same way, explains why the questions are asked, and states plainly that answering is optional.
Multimodal screening, combining portal, tablet, and phone options, tends to increase both reach and patient comfort while reducing the load on frontline staff during high-volume periods, according to implementation research on SDOH data collection in community health centers.
Role clarity matters as much as the tool itself. The clinician identifies and documents the need. The navigator or CHW owns resource matching and follow-up. A data steward, often a quality or population health staff member, owns the coded data and reporting output. Qualitative work on family medicine team perspectives on SDOH screening found that staff experience real emotional burden when they identify a need they cannot act on, and that programs hold up better when referral pathways and role boundaries are explicit from the start.
Pro Tip: Give patients an explicit opt-out option in your intro script. Consent that feels voluntary produces more honest disclosure than a screening presented as mandatory.
Embedding the screener in your EHR and mapping the codes
Discrete data capture, not free text, is what makes an SDOH screening workflow reportable. Each screening item should map to a LOINC code, and each positive response that becomes a documented social need should carry an ICD-10 Z-code on the problem list so the need is visible to any clinician who opens the chart later.
- Build the screener as a structured form or flowsheet rather than a scanned PDF, so responses populate discrete fields.
- Use pre-visit questionnaires synced to the portal when your EHR supports it, cutting rooming time.
- Add clinical decision support that flags a positive screen and suggests a referral order set at the point of documentation.
- Export coded fields on a schedule that feeds your outcomes dashboard and any MIPS reporting extract, rather than requiring manual chart review.
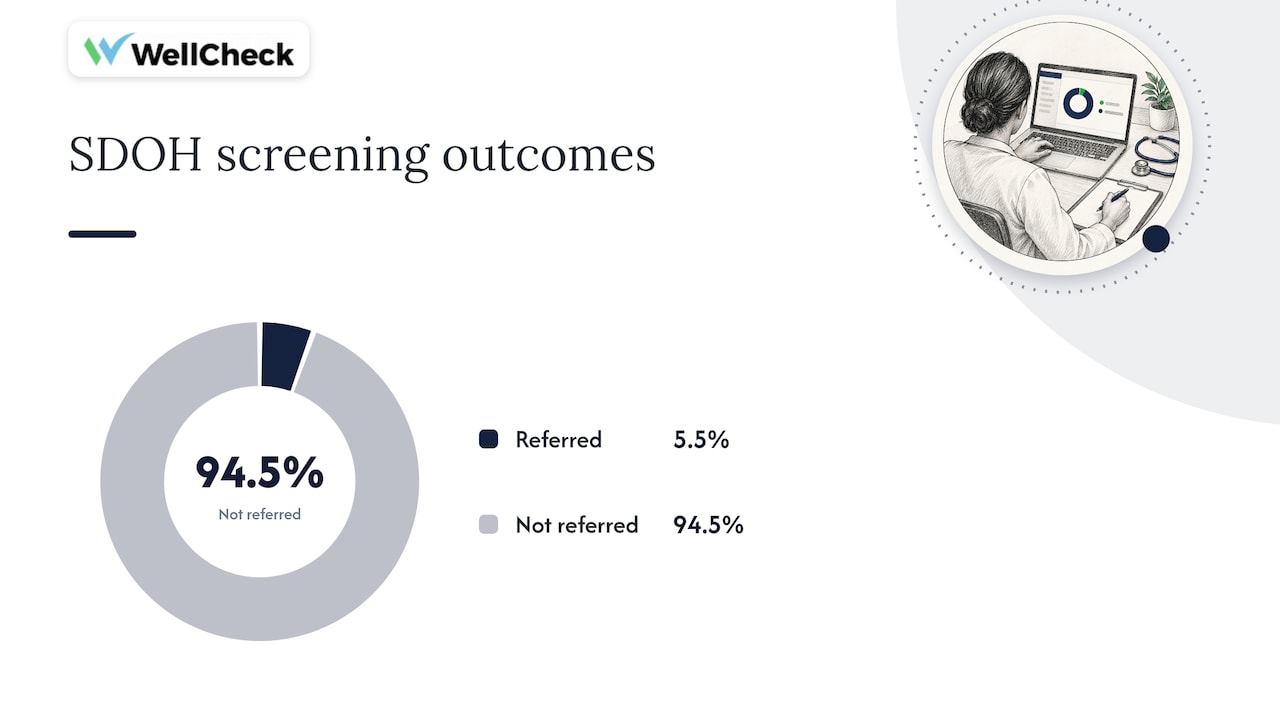
One Epic-integrated SDOH solution screened 111,486 beneficiaries and referred 6,103 high-risk beneficiaries over three years, a scale that implementation data from EHR-integrated screening shows was possible because the screener was embedded directly into existing pre-visit workflows rather than run as a separate process. That kind of volume depends on discrete capture: a program cannot report screening reach or referral rates from unstructured notes.
Good documentation practice extends past coding into the note itself. Clear, audit-ready shared care notes make it easier for any team member, or an auditor, to reconstruct what was asked, what was found, and what happened next, a discipline covered in more detail in this clinician checklist for shared care notes.
Designing a referral path that actually closes
A closed-loop referral is one where the sending team knows whether the patient reached the community service provider (CSP) and whether the need was resolved, not just that a referral was sent. Without that visibility, programs can report screening volume but nothing about follow-through, which leaves staff unsure whether their work matters and leaves funders without the outcome data they ask for.
Routing logic should prioritize safety first. A positive screen for interpersonal safety or housing instability with an imminent risk flag should route to a navigator or social worker the same day, while lower-urgency needs like transportation or utility assistance can follow a standard queue. CMS measure guidance for Measure 487 and Measure 498 sets a 60-day expectation for documented contact between a patient who screens positive and a community service provider, which is a reasonable outer bound for your own follow-up timeline even outside formal measure reporting.
Every referral needs status fields that a navigator updates as the case moves, not just a closed or open flag:
- Referral sent: the date and CSP the referral went to.
- Contact attempted: the date and method of the first outreach.
- Contact made: confirmation the patient and CSP connected.
- Services provided: what the CSP delivered.
- Resolved or unresolved: the final status, with a reason if unresolved.
Automated reminders to partner organizations reduce the manual follow-up burden on navigators, an approach that EHR-integrated referral tracking research ties to sustained referral volume without proportional staff growth. For a deeper walkthrough of routing design and documentation expectations, see our guide to closed-loop referral systems.
Aligning your metrics with CMS measures and program goals
CMS Measure 487 covers screening itself: the numerator counts patients 18 and older who were screened for the five core HRSN domains during the reporting period, against a denominator of eligible patients seen. Measure 498 covers what happens next: it counts patients who screened positive and had documented contact with a community service provider, generally within 60 days, against the denominator of patients who screened positive. Both measures come from the 2025 QPP measure specifications, and reporting accuracy depends entirely on the discrete data capture described earlier in this guide.
Beyond the measures themselves, a handful of operational KPIs tell you whether the workflow is functioning day to day.
| Metric | What it tracks |
|---|---|
| Screening rate | Share of eligible patients screened in the reporting period |
| Positive-screen rate | Share of screens that identify at least one need |
| Referral acceptance rate | Share of referrals the patient agrees to pursue |
| Contact with CSP within 60 days | Share of positive screens with documented CSP contact |
| Closed-loop completion rate | Share of referrals resolved with a documented outcome |
Dashboards showing both improving and declining trends, not just favorable ones, tend to be more persuasive to leadership than a report that only shows success, based on implementation summaries on SDOH program sustainability. Periodic audits of coded data against chart review catch the gaps that dashboards alone can miss. More on selecting the right outcome metrics for funder reporting is available in our metrics guide for directors.
Anticipating the barriers that stall most pilots
Staff burden is the most common reason SDOH screening workflows stall after a strong launch. Splitting responsibility clearly, clinicians identify needs, navigators or CHWs handle resource linkage, keeps any single role from absorbing the full weight of a positive screen, and it directly addresses the distress documented among frontline teams screening for social needs who lack a clear path to act on what they find.
- Train staff on the intro script and the referral handoff before go-live, not after the first difficult conversation.
- Coordinate with community partners ahead of launch so referral volume does not exceed what they can absorb.
- Keep an opt-out option visible in every screening modality to protect patient trust.
- Assign a clinic champion to run brief weekly check-ins on what is and is not working.
Programs that start with one domain or one clinic and adjust through PDSA cycles sustain screening longer than those that mandate broad universal screening on day one, according to system-level implementation research. A nine-step framework for sequencing a referral rollout, including pilot scope and partner onboarding, is laid out in our referral implementation plan.
Pro Tip: Set a referral volume ceiling with your community partners before launch. Overwhelming a food pantry or housing agency in week one damages the relationship you need for month twelve.
What the evidence says about closing the loop
Programs that embed screening into existing visit workflows and track referrals through discrete status fields report meaningfully higher screening reach than those relying on manual or paper-based processes, as shown in the Epic-integrated SDOH implementation referenced earlier in this guide. The common thread across the implementation literature cited throughout this article is structural: standardized tools, coded data, and defined status fields, not additional staff, are what let a screening program scale.
A rural health hub deployment with a multi-partner ecosystem, including both clinical and social services referrals, recorded 22,682 individuals screened, 45,458 services delivered, and a 93.9% closed-loop completion rate. Teams building toward that kind of accountability generally need three things in place: status fields on every referral, an outcomes dashboard leadership can review without a manual report request, and training that gets navigators and CHWs comfortable with the workflow before volume increases.
- Define status fields (sent, contacted, connected, resolved) before your first patient is screened.
- Build a dashboard view for screening rate, referral acceptance, and closed-loop completion.
- Train navigators and CHWs on scripting and escalation before go-live, not during it.
How EquiLoop and Workforce Development Academy can support your rollout
Most programs do not fail at screening. They fail at tracking what happened after the referral went out, and that gap is exactly what EquiLoop is built to close. EquiLoop manages the full workflow from SDoH screening and intake through referral routing, status tracking, and funder-ready outcomes dashboards, and it is configured around the partner network and reporting requirements your organization already has rather than asking you to rebuild around a new system.
- Screening and intake data feed directly into referral routing and status tracking.
- Outcomes dashboards support Measure 487 and Measure 498 reporting without manual chart pulls.
- Workforce training and credentialing options are available for navigators and community health workers handling referral follow-up.
If your team is weighing how to close the referral loop without adding headcount, a 30-minute conversation can clarify what a configured deployment would look like for your organization. Schedule a demo to walk through your current workflow and referral pathways.
Sources
For teams building or auditing a screening workflow, these sources are worth keeping on hand: the AHC HRSN Screening Tool for core domains and LOINC mapping, the 2025 Measure 487 specification for reporting logic, and the EHR-integrated screening implementation study for a working model of scale without added staff. The family medicine team perspectives study and system approaches summary round out the staffing and sustainability picture.
- System approaches to social determinants of health screening and intervention innovation
- Accountable Health Communities (AHC) HRSN Screening Tool (companion and core tool)
- 2025 Measure 487: Screening for Social Drivers of Health (QPP)
FAQ
How do you screen for SDOH in a clinical setting?
Screening for SDOH involves administering a standardized tool, such as the AHC HRSN Screening Tool or PRAPARE, at a consistent point in the visit, capturing responses as discrete EHR data, and routing any positive result to a navigator or CHW for follow-up. The workflow should include a clear intro script, an opt-out option, and defined roles for who screens, who scores, and who manages referrals.
What are the five main categories of SDOH?
The AHC HRSN Screening Tool defines five core domains: living situation, food insecurity, transportation, utility needs, and interpersonal safety. Many programs add supplemental domains, such as employment or social isolation, depending on their patient population and reporting goals.
What SDOH screenings does CMS require for MIPS reporting?
CMS reporting under MIPS centers on Measure 487 and Measure 498: Measure 487 tracks whether eligible patients were screened for the five core HRSN domains, and Measure 498 tracks whether patients who screened positive had documented contact with a community service provider, typically within 60 days. Both measures depend on discrete, coded screening and referral data rather than free-text notes.
What screening tools does CMS recognize for SDOH?
The Accountable Health Communities HRSN Screening Tool is the primary CMS-associated instrument, built around the five core domains with LOINC-mapped items for standardized data exchange. PRAPARE is widely used alongside it, particularly in community health centers that want broader domain coverage for care planning beyond measure reporting.

